
The GLP-1 Era: How Weight-Loss Medicines Are Changing the Way We Think About Food

The emergence of glucagon-like peptide-1 (GLP-1)-based medicines represents one of the most consequential developments in contemporary obesity medicine. Drugs based on GLP-1 receptor agonism, as well as newer dual GLP-1/GIP therapies, have moved weight management beyond a predominantly behavioural framework toward a model in which pharmacological treatment can become part of long-term clinical care. This transition is significant not only because these medicines can produce substantial reductions in body weight, but because they alter a fundamental biological experience: hunger.
For decades, public discussions about weight management frequently centred on discipline, calorie restriction, willpower and individual responsibility. The growing use of GLP-1 therapies challenges that framework by demonstrating more clearly that appetite is regulated by complex physiological systems involving hormones, the gastrointestinal tract, the brain and metabolic signalling. In December 2025, the World Health Organization (WHO) issued its first global guideline specifically addressing GLP-1 therapies for obesity, describing obesity as a chronic, relapsing disease and recommending that pharmacological treatment be considered as part of comprehensive care rather than as an isolated intervention.
From Dieting to the Medical Treatment of Obesity
The most important conceptual shift associated with GLP-1 medicines is the gradual movement from viewing obesity primarily as a matter of lifestyle behaviour toward recognizing it as a chronic medical condition requiring potentially long-term management. The WHO estimates that more than one billion people globally live with obesity and emphasizes that its causes involve interactions between genetics, neurobiology, eating behaviour, food environments, socioeconomic conditions and broader societal factors.
This does not make diet and physical activity irrelevant. Rather, it changes their position within the treatment model. Medicines such as semaglutide and tirzepatide are authorized for weight management alongside reduced-calorie diets and increased physical activity. The European Medicines Agency (EMA), for example, specifies these conditions in its authorizations for Wegovy and Mounjaro.

The WHO's 2025 guideline consequently presents GLP-1 therapy as one component of a broader intervention that can include nutritional counselling, physical activity and behavioural support. Its recommendations are conditional, reflecting continuing uncertainty concerning long-term treatment, discontinuation, affordability, health-system preparedness and equitable access.
This is an important distinction. The arrival of GLP-1 therapy does not represent the end of dieting or lifestyle medicine. It represents a recognition that for some people, biological regulation of appetite may require medical intervention in the same way that other chronic conditions require pharmacological support.
Appetite, Portion Size and the Changing Experience of Food
GLP-1 therapies influence eating behaviour partly by reproducing or amplifying physiological signals associated with satiety. GLP-1 is a naturally occurring hormone involved in glucose regulation and appetite control. Pharmacological GLP-1 signalling can increase insulin secretion when blood glucose is elevated, reduce glucagon secretion, slow gastric emptying and increase feelings of fullness. The practical consequence is often a reduction in spontaneous food intake.
This mechanism has implications extending beyond the number on a weighing scale. For many patients, food can become less psychologically dominant because physiological hunger and appetite are reduced. Portion sizes may become smaller, snacks may become less compelling, and highly energy-dense foods may lose some of their previous appeal. In this sense, GLP-1 treatment can change the relationship between appetite and decision-making: instead of continuously attempting to override hunger through conscious restraint, an individual may experience less hunger in the first place.
Emerging research suggests that these changes may also influence purchasing behaviour. A 2026 study published in JAMA Network Open, involving more than 1,100 participants and over one million recorded food purchases, found that people initiating GLP-1 receptor agonists subsequently purchased foods with slightly lower energy density, sugar, carbohydrates and saturated fat, while protein content increased modestly. The researchers also observed a shift away from ultraprocessed foods toward less processed products.
Such findings should not be interpreted as evidence that GLP-1 medicines automatically create healthy diets. They do, however, suggest that appetite modification may influence the food environment at the level of everyday consumer behaviour. If people eat less, and if their preferences change as a consequence of altered appetite and satiety, the commercial food system may eventually have to respond.
Nutrition, Micronutrients and the Preservation of Muscle
The reduction of appetite creates a second clinical question: when people eat substantially less, are they obtaining enough nutrition?

Weight loss is not nutritionally neutral. A reduction in total food intake can reduce the intake of protein, vitamins, minerals, fibre and other essential nutrients if food quality is not carefully considered. Gastrointestinal adverse effects associated with GLP-1 therapies, including nausea, vomiting, diarrhoea and constipation, can further complicate food intake for some patients. Consequently, nutritional management is becoming an increasingly important component of obesity treatment.
The issue of muscle mass deserves particular attention. Weight loss generally involves reductions in both fat mass and lean mass, and GLP-1 therapies are not an exception. A 2025 systematic review and network meta-analysis of randomized controlled trials found that GLP-1-based treatments reduced total body weight and fat mass while also producing a measurable reduction in lean mass, with lean mass accounting for approximately one-quarter of total weight loss in the analysed studies.
More recent 2026 evidence continues to emphasize this issue. A systematic review and meta-analysis published in Diabetes, Obesity and Metabolism found that lean mass represented approximately 25–39% of total weight lost with different incretin therapies, while lifestyle interventions showed broadly comparable proportional lean-mass loss. Importantly, the analysis found a more favourable profile when resistance training was incorporated into weight-management programmes.
This changes the definition of successful weight management. Losing kilograms is not necessarily the same as improving physical health. Contemporary treatment should increasingly ask what proportion of weight loss represents adipose tissue, what happens to muscle strength and physical function, and whether nutritional intake is sufficient to support long-term health.
Recent clinical nutrition literature therefore places increasing emphasis on adequate protein intake, micronutrient monitoring, resistance exercise and, where appropriate, body-composition assessment during GLP-1 treatment. The emerging model is consequently not simply “take a medicine and eat less,” but rather “use pharmacological appetite regulation while protecting nutritional adequacy and physical function.”
What the GLP-1 Era Means for the Food Industry
The implications extend beyond hospitals and medical practices. If GLP-1 medicines become increasingly common, food manufacturers and retailers may encounter a consumer population that is simultaneously smaller in appetite and more selective in what it considers worth eating.
The traditional food economy has often depended on volume, convenience, palatability and repeat consumption. A consumer who becomes satisfied after a smaller portion represents a different commercial proposition. Products traditionally designed around large portions, frequent snacking or high energy density may face new pressures, while foods that offer greater nutritional value in smaller quantities may become more attractive.
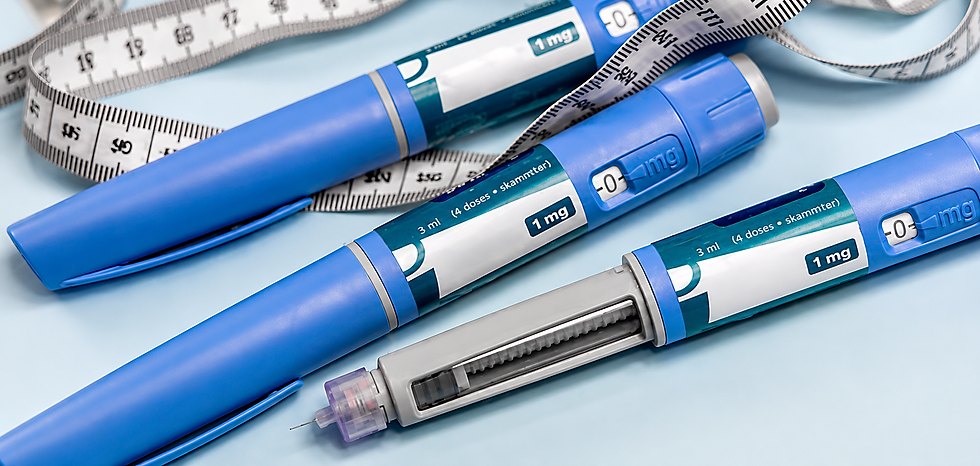
The emerging market response is already beginning to reflect this possibility. Research showing changes in food purchasing among GLP-1 users suggests that pharmaceutical appetite regulation could influence demand patterns beyond the clinic. Food companies may consequently have incentives to develop smaller portions, higher-protein products, nutrient-dense meals and products designed around satiety rather than simply maximizing consumption.
Nevertheless, the food industry should not interpret GLP-1 therapy as a substitute for public-health nutrition. Obesity remains strongly influenced by food accessibility, pricing, marketing, urban environments and socioeconomic circumstances. Pharmaceutical treatment may modify individual appetite, but it cannot independently redesign the environments in which populations make dietary decisions.
What It Means for Healthcare Systems
Healthcare systems face an equally substantial transformation. The WHO's decision to issue a global guideline signals that GLP-1 treatment is moving into the territory of public-health policy rather than remaining solely a pharmaceutical innovation. In 2026, WHO began developing implementation guidance to help countries determine how GLP-1 therapies could be integrated into multimodal obesity care and how limited resources might be allocated according to expected health benefit.
The question is therefore no longer simply whether these medicines work. Health systems must also determine who should receive them, how long treatment should continue, how patients should be monitored, how nutritional care should be integrated, how equitable access can be achieved and how healthcare professionals should respond when treatment is discontinued.

Regulatory developments are also continuing. In Europe, the EMA's Committee for Medicinal Products for Human Use recommended in May 2026 an oral tablet formulation of semaglutide for weight management, illustrating how rapidly the therapeutic landscape is expanding beyond injectable treatment. In the United States, the FDA continues to regulate the rapidly evolving GLP-1 market, including issues concerning compounded versions of semaglutide, tirzepatide and liraglutide.
The resulting healthcare model is likely to become increasingly multidisciplinary. Physicians, dietitians, pharmacists, exercise professionals and behavioural-health specialists may all have roles in ensuring that pharmacological weight reduction translates into sustainable improvements in health rather than simply lower body weight.
A New Definition of Eating
The deeper significance of the GLP-1 era may ultimately be cultural. For generations, modern societies have treated hunger as both a biological necessity and a personal test of discipline. GLP-1 therapies introduce a different proposition: appetite can be medically modified, and doing so can alter not only body weight but the subjective experience of eating.
This development should neither be celebrated as a universal solution nor dismissed as a pharmaceutical shortcut. The WHO explicitly stresses that medication alone cannot reverse the global obesity challenge. Instead, GLP-1 therapy should be understood within a broader framework encompassing nutrition, physical activity, behavioural support, equitable healthcare and healthier food environments.
The central question of the GLP-1 era is therefore not simply how much weight a person can lose. It is what happens to the quality of life, nutritional status, muscle health, eating behaviour and long-term relationship with food while that weight is being lost.
If the first era of modern dieting asked people to control their appetite through discipline, the GLP-1 era asks medicine, nutrition science and society to understand appetite more precisely. That distinction may prove to be one of the most important changes in how contemporary healthcare approaches obesity, and, ultimately, how society thinks about food itself.


Comments